Healthcare leadership coaching: for the clinician in charge
Healthcare leadership coaching explained: why clinician-leaders need it, what good engagements cover, coaching vs. training, and how to choose a coach.
Healthcare leadership coaching exists because of a promotion pattern the industry runs at scale: take the best clinician, make them the leader, provide nothing in between. The new medical director, charge nurse, or service-line chief arrives carrying an identity built on clinical mastery — and a job that suddenly runs on delegation, difficult conversations, and leading people across professional lines. Coaching is the market’s answer to that gap, and most of what’s published about it is written by the coaches. Here’s the buyer’s version: what the work actually is, what good engagements cover, and how to choose.
The identity problem coaching actually works on
The clinician-to-leader transition is harder than the generic manager transition, for a reason worth naming precisely: clinical culture trains its people that competence is displayed and uncertainty is dangerous — excellent preparation for the OR, poisonous preparation for learning a new craft in public. The new clinician-leader therefore faces a double bind: the leadership job requires being a visible beginner (at coaching, at conflict, at running the room), while the professional identity forbids exactly that.
This is why one-to-one coaching earns its place in healthcare specifically: it’s a confidential venue for beginnerhood — the one room where the medical director can say “I don’t know how to have this conversation with my former peer” without spending credibility. A good coach works both layers at once: the skill (the conversation’s actual mechanics) and the identity (what kind of excellence this new role rewards — a shift from being the best responder in the room to building the room that responds).
What a good engagement covers
The recurring curriculum, across well-run healthcare coaching engagements:
- The delegation ladder — moving from doing to transferring ownership, hardest for leaders whose hands were their value.
- Conversations across hierarchy — feedback to a senior physician, accountability with a former peer, the behavior-impact structure that keeps both survivable.
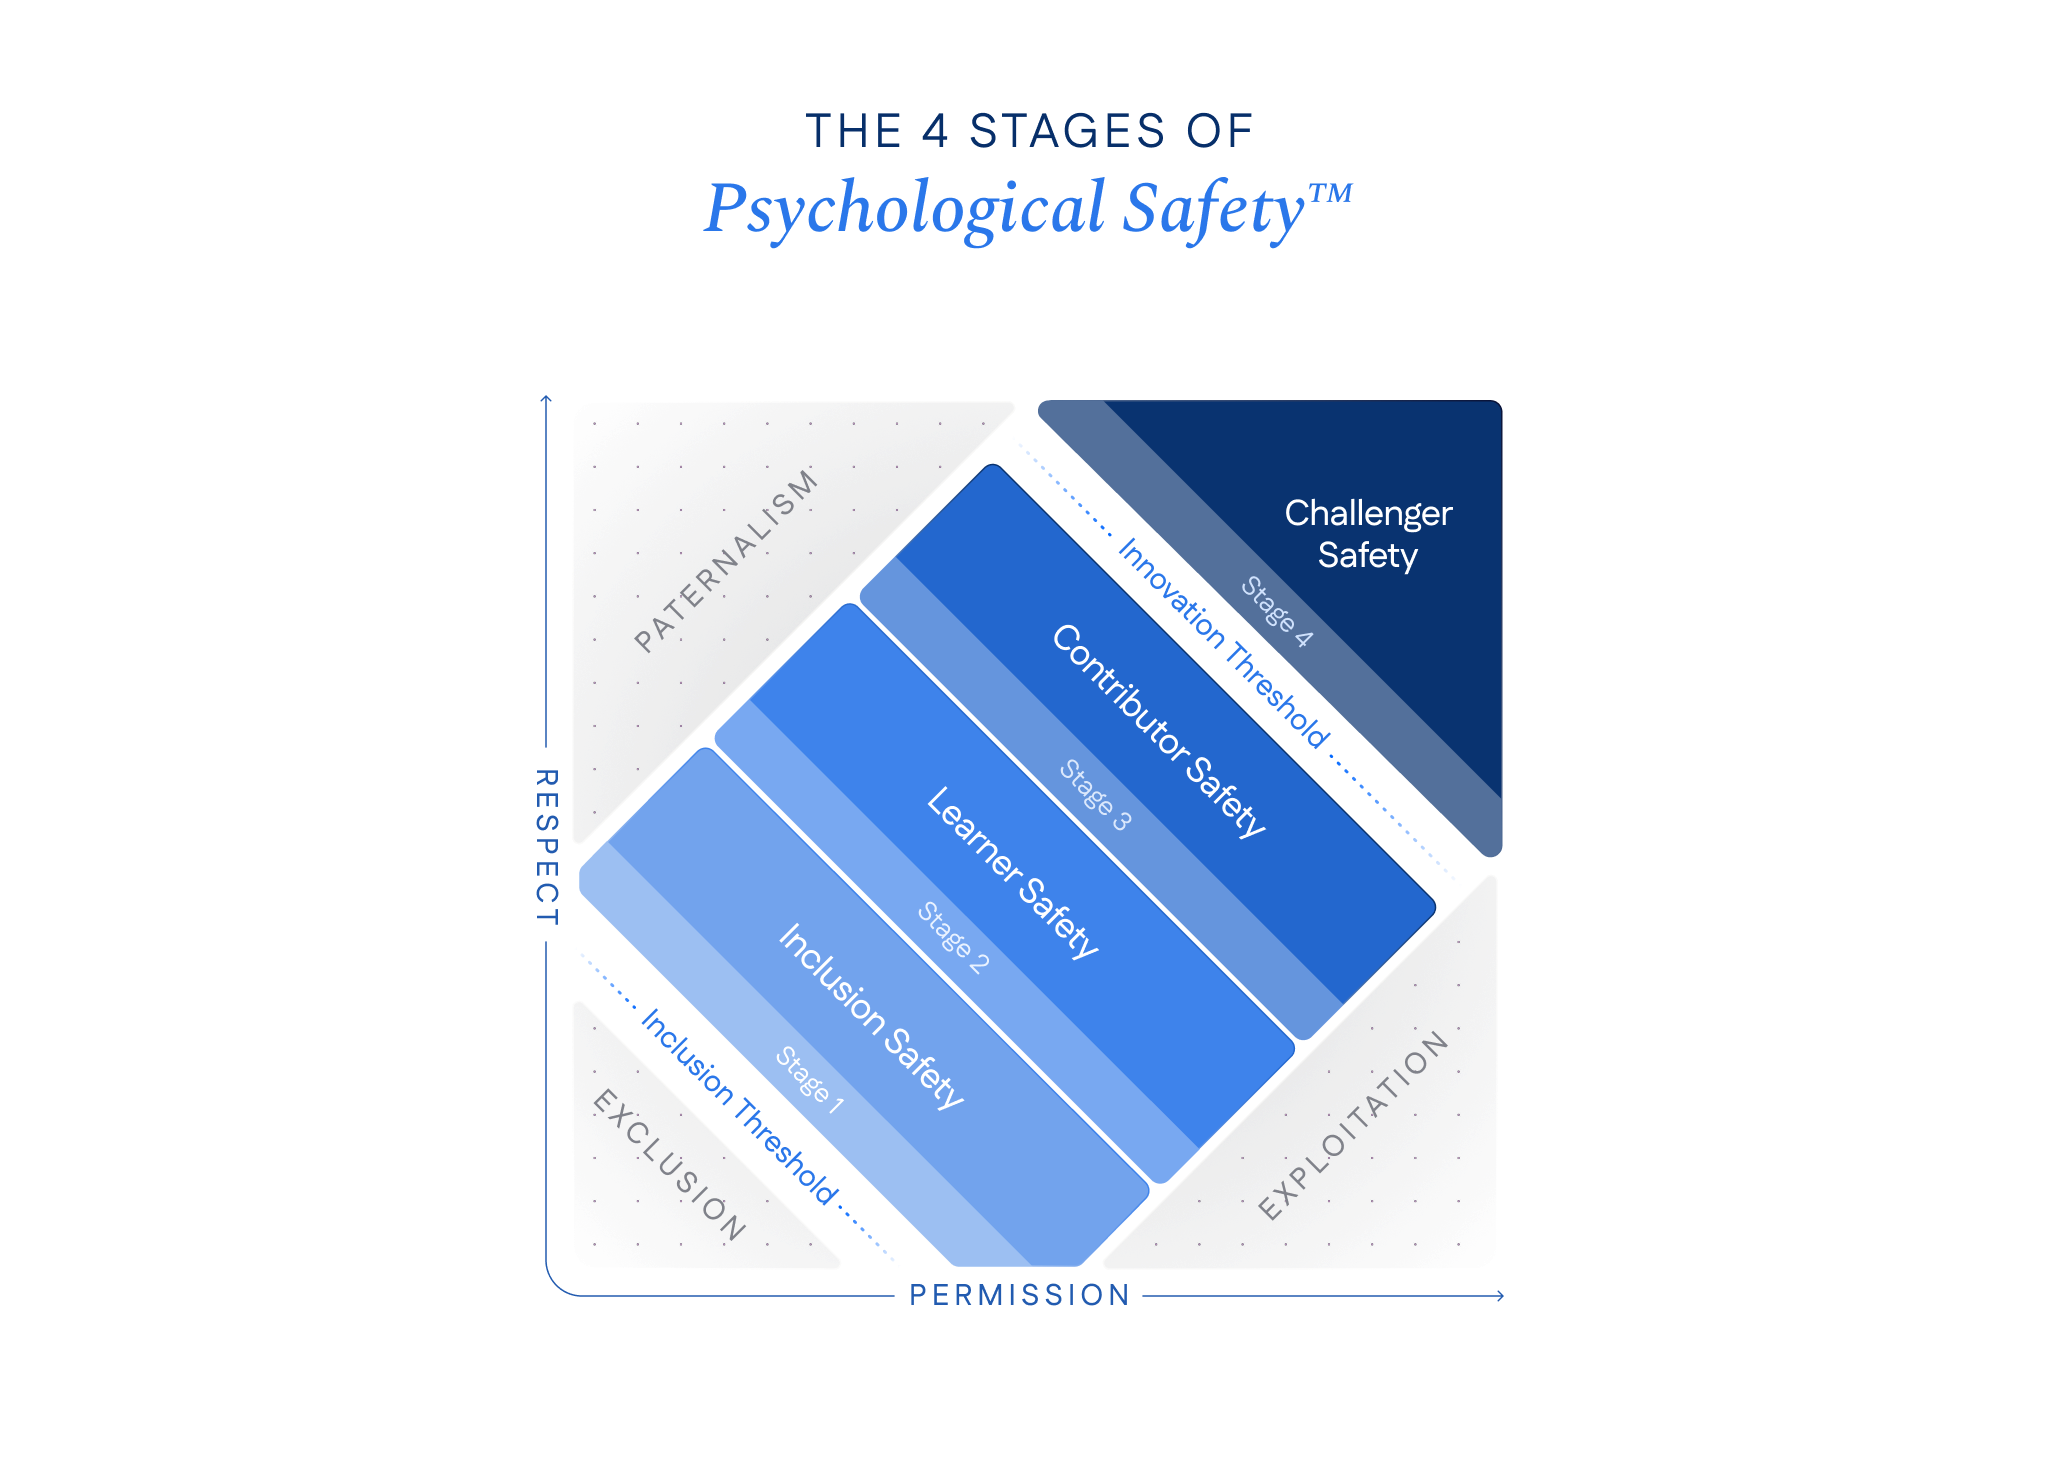
- Building voice on their unit — the leader’s own responses to flags, questions, and pushback, practiced deliberately, because a clinician-leader’s reaction to the first challenge prices every future one.
- Leading the change load — protocol rollouts and system migrations, with actual change discipline rather than clinical authority alone.
- Sustainability — energy, boundaries, and the emotional labor of leading exhausted teams; not wellness garnish but role viability.
And underneath all five, the good engagements share machinery: a baseline (ideally a real instrument, sometimes a 360), defined behavioral goals, and a re-measure — because coaching without evidence is expensive conversation, in healthcare as everywhere.
Coaching, training, or both
The honest sorting, since vendors sell whichever they have: coaching is deep, individual, confidential — right for senior stakes, individual struggles, and the identity work above. Training builds shared capability at cohort scale — frameworks, common language, practice and measurement — and is the better first dollar when the gap is organizational (thirty new nurse managers need the same coaching skills; thirty coaches is a strange way to deliver one curriculum). The strong pattern pairs them: the program supplies framework and instrument; coaching personalizes it for the leaders whose situations demand depth. What to avoid is coaching prescribed as the universal remedy because it’s the easiest engagement to buy one of.
Choosing the coach: vet like any leadership consulting purchase, plus the context test. Method questions first — what framework, what measurement, what does a typical arc produce? Then healthcare fluency: can they speak credibly about hierarchy gradients, regulatory reality, and what a unit at 2 a.m. is actually like? (Clinical experience isn’t mandatory; earned fluency is.) References from comparable roles, and one disqualifying tell: a coach who can’t describe what the leader’s team will experience differently is selling sessions, not change.
It’s a Wednesday in January at a regional health system in Spokane, and the new chief of hospital medicine — eleven years a superb hospitalist, eleven weeks a struggling chief — is in her third coaching session, rehearsing a conversation she’s postponed twice: telling her group’s most senior physician that his behavior in huddles is silencing the residents. The coach makes her run it aloud four times, each pass more behavioral and less apologetic. Thursday she has it — imperfectly, survivably. What she reports back isn’t triumph; it’s the residents’ next huddle, where two of them spoke. “I thought coaching would make me feel like a leader,” she says. “It made me do one thing a leader does. Apparently that’s the order it goes in.”
It is. If you’re buying: insist on that order — behaviors first, feelings downstream, evidence throughout. If you’re the clinician-leader: the beginnerhood is temporary, the skills are learnable, and the confidential room is a legitimate place to start.
Frequently asked questions
- What is healthcare leadership coaching?
- One-to-one development for leaders in care settings — medical directors, nursing leaders, service-line chiefs, administrators — typically working the transition from clinical excellence to leading through others: delegation, difficult conversations, leading across hierarchy, and building teams where staff speak up.
- Why do clinician-leaders need coaching?
- Because the promotion usually rewards the wrong excellence: superb clinicians become leaders with no leadership development, in a culture where admitting you're learning feels dangerous. Coaching gives them a confidential venue to build the new capability without performing mastery they don't yet have.
- What is the difference between coaching and leadership training in healthcare?
- Training builds defined capability in cohorts — frameworks, practice, measurement — and scales. Coaching works one leader's specific situation confidentially and deeply. They pair well: programs supply the shared framework and instrument; coaching personalizes the practice for leaders whose stakes or struggles are individual.
- How do you choose a healthcare leadership coach?
- Vet method plus context: a real coaching framework and measurement approach, credible fluency in clinical environments — hierarchy, regulatory reality, the physician-nurse dynamic — references from comparable roles, and a clear answer to what changes for the leader's team, not just the leader's feelings.